炎症Inflammation · 骨骼肌 · 骨骼肌肉系统 · NTP ntp-0590
诊断要点:每当炎症被视为原发性病变时,应诊断并分级。如果炎症特别严重或相对于原发性病变的严重程度比预期更严重,则可诊断为继发性病变(例如继发于坏死)。
病变描述
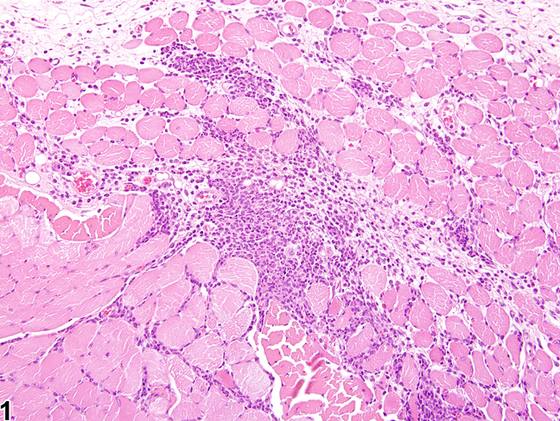
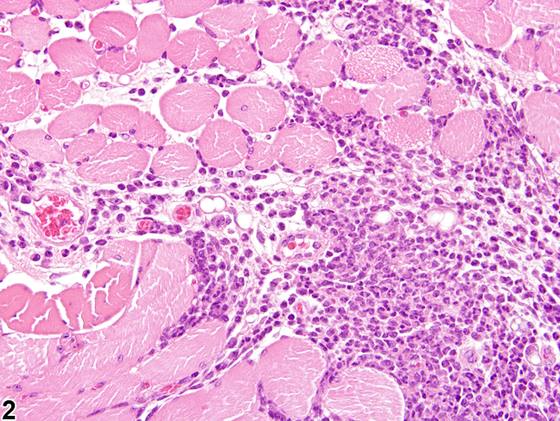
骨骼肌炎症可由多种类型的损伤引起,包括物理性创伤(例如注射部位、咬伤和钝器伤)、暴露于肌毒素或感染性病原体,以及缺血、血栓形成或肌纤维坏死。炎症可表现为多种形态学模式。它可以是主要为间质性的,伴有很少或无肌纤维坏死,或者可以是主要特征,而炎症很少。在NTP研究中,炎症有五个标准类别:急性(急性(acute))、化脓性(化脓性(suppurative))、慢性(慢性(chronic))、慢性活动性(慢性活动性(chronic-active))和肉芽肿性(肉芽肿性(granulomatous));脓肿诊断为化脓性炎症。在急性炎症(Figure 1、Figure 2)中,主要浸润细胞是中性粒细胞(neutrophil),尽管也可能存在较少的巨噬细胞(macrophage)和淋巴细胞(lymphocyte)。也可能有水肿或充血(hyperemia)的证据。中性粒细胞也是化脓性炎症(Figure 3、Figure 4)中的主要浸润细胞类型,但中性粒细胞聚集,其中许多发生变性(化脓性渗出物,化脓性 exudate)。细胞碎片(来自驻留细胞群和浸润白细胞)、含纤维蛋白(fibrin)的蛋白性液体、较少的巨噬细胞、偶见的淋巴细胞和/或浆细胞(plasma cell),以及可能的感染性病原体也可能存在于渗出物中。肉眼上,这些病变将以脓液的存在为特征。在渗出物周围的组织中,可能存在成纤维细胞(fibroblast)、纤维结缔组织和混合性炎症细胞,取决于病变的慢性程度。淋巴细胞在慢性炎症中占主导地位。淋巴细胞在慢性活动性炎症中也占主导地位,但也存在显著数量的中性粒细胞(Figure 5、Figure 6)。两种病变均可能含有巨噬细胞。肉芽肿性炎症是慢性炎症的另一种形式,但该诊断需要存在显著数量的聚集性、大的、活化的巨噬细胞、上皮样巨噬细胞(epithelioid macrophage)或多核巨细胞(multinucleated giant cell)(Figure 7、Figure 8)。由于炎症可响应于或导致肌纤维坏死,除水肿和/或出血外,肌病性改变常同时发生。炎症反应对于有效修复受损组织是必要的;然而,该反应的性质、持续时间和强度将关键性地影响修复的总体结局。
诊断与分级建议(NTP 共识)
每当炎症被视为原发性病变时,应诊断并分级。如果炎症特别严重或相对于原发性病变的严重程度比预期更严重,则可诊断为继发性病变(例如继发于坏死)。诊断应包括炎症类型(例如急性、慢性、慢性活动性)作为修饰词。通常不需要包括部位修饰词,除非需要区分两个不同的病变。相关病变,如血管病变、异物或感染性病原体,应单独诊断。继发于炎症的病变(例如坏死)和属于炎症过程一部分的病变(例如水肿或出血)不应单独诊断,除非严重程度需要,但应在病理学叙述中描述。
图谱
英文原文
展开 NTP 官方英文描述与建议
Comment:
Inflammation of skeletal muscle can occur as a result of numerous types of injury, including physical trauma (e.g., injection sites, bite wounds, and blunt trauma), exposure to myotoxins or infectious agents, and ischemia, thrombosis, or myofiber necrosis. Inflammation can exhibit various morphologic patterns. It can be primarily interstitial, with little or no myofiber necrosis, or can be the predominant feature, with little inflammation. In NTP studies, there are five standard categories of inflammation: acute, suppurative, chronic, chronic-active, and granulomatous; abscesses are diagnosed as suppurative inflammation. In acute inflammation ( Figure 1 and Figure 2 ), the predominant infiltrating cell is the neutrophil, though fewer macrophages and lymphocytes may also be present. There may also be evidence of edema or hyperemia. The neutrophil is also the predominant infiltrating cell type in suppurative inflammation ( Figure 3 and Figure 4 ), but the neutrophils are aggregated, and many of them are degenerate (suppurative exudate). Cell debris (both from the resident cell populations and from infiltrating leukocytes); proteinaceous fluid containing fibrin, fewer macrophages, occasional lymphocytes, and/or plasma cells; and possibly an infectious agent may also be present within the exudate. Grossly, these lesions would be characterized by the presence of pus. In the tissue surrounding the exudate, there may be fibroblasts, fibrous connective tissue, and mixed inflammatory cells, depending on the chronicity of the lesion. Lymphocytes predominate in chronic inflammation . Lymphocytes also predominate in chronic-active inflammation , but a significant number of neutrophils are also present ( Figure 5 and Figure 6 ). Both lesions may contain macrophages. Granulomatous inflammation is another form of chronic inflammation, but this diagnosis requires the presence of a significant number of aggregated, large, activated macrophages, epithelioid macrophages, or multinucleated giant cells ( Figure 7 and Figure 8 ). Since inflammation can occur in response to, or result in, myofiber necrosis, myopathic changes in addition to edema and/or hemorrhage often occur concurrently. An inflammatory response is necessary to effectively repair damaged tissues; however, the nature, duration, and intensity of this response will crucially influence the overall outcome of repair.
Recommendation:
Inflammation should be diagnosed and graded whenever it is considered a primary lesion. It may be diagnosed as a secondary lesion (e.g., secondary to necrosis) if it is particularly severe or more severe than expected relative to the severity of the primary lesion. The diagnosis should include the type of inflammation (e.g., acute, chronic, chronic-active) as a modifier. Generally it is not necessary to include a site modifier unless it is needed to separate two distinct lesions. Associated lesions, such as vascular lesions, foreign bodies, or infectious agents, should be diagnosed separately. Lesions secondary to the inflammation (e.g., necrosis) and lesions that are part of the inflammatory process (e.g., edema or hemorrhage) should not be diagnosed separately unless warranted by severity but should be described in the pathology narrative.
来源与引用
原始条目:https://ntp.niehs.nih.gov/atlas/nnl/musculoskeletal-system/skeletal-muscle/Inflammation
图谱总目录:NTP Nonneoplastic Lesion Atlas。 内容属美国联邦政府作品(公有领域),可引用;引用时请标注来源。
建议引用格式:NTP Nonneoplastic Lesion Atlas. Inflammation (skeletal-muscle). LabSmart 中文版:
https://www.labsmart.cn/ntp/skeletal-muscle-inflammation.html
中文图谱总页(可展开对照全部 595 条):https://www.labsmart.cn/ntp-atlas.html#skeletal-muscle-inflammation