关节炎症Joint Inflammation · 骨 · 骨骼肌肉系统 · NTP ntp-0570
诊断要点:当存在时,该病变应被诊断并给予严重程度分级。此外,炎症类型(急性、化脓性、慢性、慢性活动性或肉芽肿性)应作为修饰词纳入诊断。
病变描述
大多数关节炎症(关节炎)(Figure 1、Figure 2、Figure 3、Figure 4、Figure 5、Figure 6、Figure 7、Figure 8)累及腿和足的远端关节(跗骨、腕骨、跖骨、掌骨)。其特征为炎性细胞浸润;关节腔及相关结缔组织内蛋白性物质和纤维蛋白;滑膜增生、水肿和纤维化;以及反应性新骨形成。炎症可导致增厚的滑膜覆盖关节面(血管翳),或通过侵蚀软骨下骨破坏关节软骨。当炎症呈慢性且严重时,可导致骨赘形成和关节强直(融合)。与骨关节炎(退行性关节病;见Bone - Joint - Degeneration)不同,微生物感染所致的关节炎伴有大量液体和关节腔内纤维蛋白性渗出物。当单个关节受累时,穿透性创伤是最可能的原因,尽管微生物也可通过从邻近组织蔓延或经血流进入关节。感染性关节炎症的原因在B6C3F1小鼠和F344大鼠中不常见。然而,穿透性创伤、打斗或其他创伤可导致累及关节或关节周围组织的局限性微生物感染。在NTP研究中,受试物暴露与关节炎症发生率增加无关。免疫抑制性化合物处理可能影响动物抵抗小的局限性感染的能力,当关节腔受累时可导致关节炎症,或引起全身播散导致多器官受累,包括多关节炎。然而,尽管与关节炎相关的病原体在啮齿类动物中已被普遍认识,但在常规毒性和致癌性研究中通常未观察到其作为关节炎症的原因。在NTP研究中,炎症有五种标准分类:急性、化脓性、慢性、慢性活动性和肉芽肿性。在急性炎症中,主要浸润细胞为中性粒细胞,但也可能存在较少的巨噬细胞和淋巴细胞。还可能有水肿或充血的表现。中性粒细胞也是化脓性炎症中的主要浸润细胞类型,但中性粒细胞聚集,其中许多发生退变(化脓性渗出物)。渗出物中还可能存在细胞碎片(来自 resident 细胞群和浸润白细胞)、含纤维蛋白的蛋白性液体、较少的巨噬细胞、偶见的淋巴细胞和/或浆细胞,以及可能的感染因子。大体上,这些病变以脓液存在为特征。在渗出物周围组织中,可能存在成纤维细胞、纤维结缔组织和混合性炎性细胞,取决于病变的慢性程度。慢性和慢性活动性炎症由成纤维细胞或纤维化的存在来确定。在慢性炎症中,主要炎性细胞通常为淋巴细胞,而在慢性活动性炎症中为淋巴细胞和中性粒细胞的混合物。两种病变也可能含有巨噬细胞。然而,正是成纤维细胞或纤维化的存在决定了病变的慢性性质。肉芽肿性炎症是慢性炎症的另一种形式,但该诊断需要存在大量聚集的、大的、活化的巨噬细胞、上皮样巨噬细胞或多核巨细胞。
诊断与分级建议(NTP 共识)
当存在时,该病变应被诊断并给予严重程度分级。此外,炎症类型(急性、化脓性、慢性、慢性活动性或肉芽肿性)应作为修饰词纳入诊断。病变的任何可能发病机制应在病理学叙述中讨论。如果关节炎症作为关节周围软组织或覆盖真皮炎症过程的蔓延而发生(Figure 3、Figure 4),则不应单独诊断,但病变范围可在叙述中描述。病变的各个组成部分(例如,滑膜增生、出血、软骨变性、坏死)除非严重程度需要,否则不应单独诊断,但应在叙述中描述。相关链接:Bone - Joint - Degeneration Bone - Joint - Degeneration
图谱
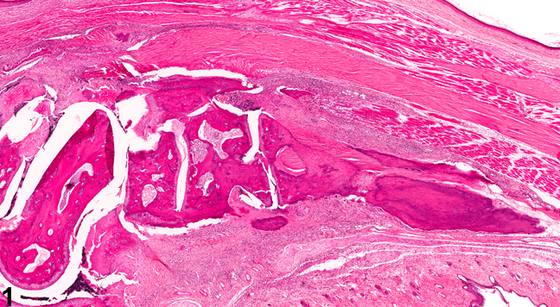
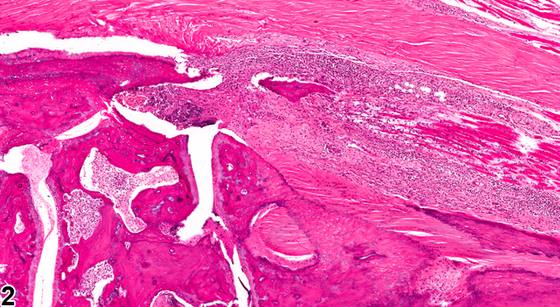
英文原文
展开 NTP 官方英文描述与建议
Comment:
Most incidences of inflammation of the joints (arthritis) ( Figure 1 , Figure 2 , Figure 3 , Figure 4 , Figure 5 , Figure 6 , Figure 7 , and Figure 8 ) involve the distal joints of the legs and feet (tarsus, carpus, metatarsus, metacarpus). They are characterized by infiltration of inflammatory cells; proteinaceous material and fibrin within the joint space and associated connective tissues; hyperplasia, edema, and fibrosis of the synovial membranes; and reactive new bone formation. Inflammation may induce thickened synovial membranes that cover the articular surfaces of the joint (pannus) or may undermine the articular cartilage by eroding subchondral bone. When chronic and severe, inflammation of the joint may lead to osteophytosis and ankylosis (fusion) of the joint. In contrast to osteoarthritis (degenerative joint disease; see Bone - Joint - Degeneration ), arthritis due to microbial infection is associated with copius fluid and fibrinous exudate within the joint space. When a single joint is affected, a penetrating wound is the most likely cause, although microbial agents may also gain access to the joint via extension from adjacent tissues or through the bloodstream. Infectious causes of joint inflammation are uncommon in the B6C3F1 mouse and F344 rat. However, penetrating wounds, fighting, or other trauma may lead to localized microbial infections involving the joint or periarticular tissues. Test article exposures have not been associated with increased incidences of joint inflammation in NTP studies. It is possible that treatment with immunosuppressive compounds may affect an animal’s ability to combat small, localized infections, which may lead to joint inflammation when the joint space is involved, or result in systemic spread leading to multiorgan involvement, including polyarthritis. However, while pathogens associated with arthritis have been recognized in rodents in general, they are not typically observed as a cause of joint inflammation in routine toxicity and carcinogenicity studies. In NTP studies, there are five standard categories of inflammation: acute, suppurative, chronic, chronic-active, and granulomatous. In acute inflammation , the predominant infiltrating cell is the neutrophil, though fewer macrophages and lymphocytes may also be present. There may also be evidence of edema or hyperemia. The neutrophil is also the predominant infiltrating cell type in suppurative inflammation , but the neutrophils are aggregated, and many of them are degenerate (suppurative exudate). Cell debris, both from the resident cell populations and from infiltrating leukocytes; proteinaceous fluid containing fibrin, fewer macrophages, occasional lymphocytes, and/or plasma cells; and possibly an infectious agent may also be present within the exudate. Grossly, these lesions would be characterized by the presence of pus. In the tissue surrounding the exudate, there may be fibroblasts, fibrous connective tissue, and mixed inflammatory cells, depending on the chronicity of the lesion. Chronic and chronic-active inflammation is determined by the presence of fibroblasts or fibrosis. With chronic inflammation , the predominant inflammatory cell is usually the lymphocyte, whereas in chronic-active inflammation it is a mixture of lymphocytes and neutrophils. Both lesions may also contain macrophages. However, it is the presence of fibroblasts or fibrosis that determines the chronic nature of the lesion. Granulomatous inflammation is another form of chronic inflammation, but this diagnosis requires the presence of a significant number of aggregated, large, activated macrophages, epithelioid macrophages, or multinucleated giant cells.
Recommendation:
When present, this lesion should be diagnosed and given a severity grade. In addition, the type of inflammation (acute, suppurative, chronic, chronic-active, or granulomatous) should be included in the diagnosis as a modifier. Any potential pathogeneses of the lesion should be discussed in the pathology narrative. If joint inflammation occurs as an extension of an inflammatory process from the periarticular soft tissues or overlying dermis ( Figure 3 and Figure 4 ), it should not be diagnosed separately, but the extent of the lesion can be described in the narrative. The individual components of the lesion (e.g., synovial hyperplasia, hemorrhage, degeneration of cartilage, necrosis) should not be diagnosed separately unless warranted by severity but should be described in the narrative. Related Links: Bone - Joint - Degeneration Bone - Joint - Degeneration
来源与引用
原始条目:https://ntp.niehs.nih.gov/atlas/nnl/musculoskeletal-system/bone/Joint-Inflammation
图谱总目录:NTP Nonneoplastic Lesion Atlas。 内容属美国联邦政府作品(公有领域),可引用;引用时请标注来源。
建议引用格式:NTP Nonneoplastic Lesion Atlas. Joint Inflammation (bone). LabSmart 中文版:
https://www.labsmart.cn/ntp/bone-joint-inflammation.html
中文图谱总页(可展开对照全部 595 条):https://www.labsmart.cn/ntp-atlas.html#bone-joint-inflammation